
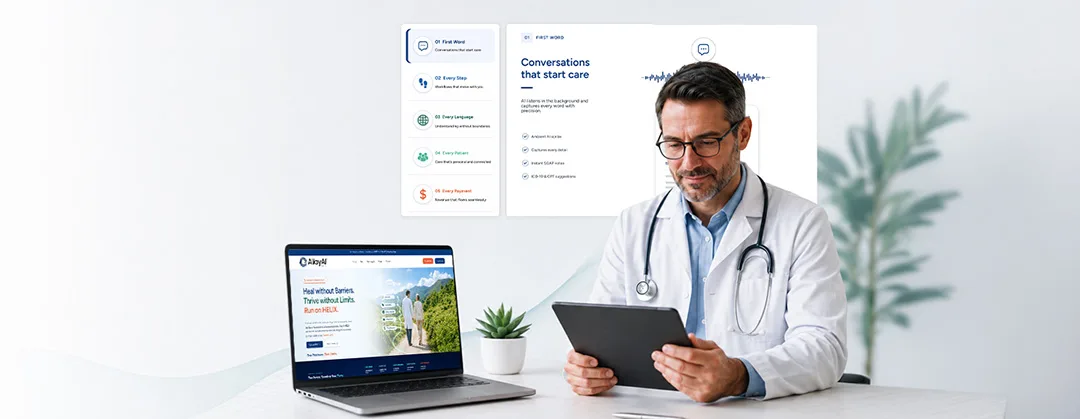
Walk into most U.S. medical practices on a Wednesday afternoon, and you’ll find the same quiet chaos behind the front desk. A nurse re-typing a patient’s history into a second system because the first one doesn’t talk to it. A biller on hold with an insurance company for the third time this week about the same denied claim. A physician finishing notes an hour after the last patient left, trying to remember details that felt obvious in the room and don’t anymore.
None of this is anyone’s fault. It’s just what happens when a practice runs on a handful of separate systems that were never built to talk to each other. That gap — between all the individual tools a clinic uses and one thing that actually connects them — is the whole reason healthcare workflow automation exists as a category in the first place.
What the Term Actually Means
It’s worth being precise here, because “automation” gets used loosely enough to mean almost anything. Healthcare workflow automation, in the way that actually matters to a practice, means the steps of a patient encounter — scheduling, documentation, coding, prior authorization, billing — move forward on their own, in sequence, without a staff member manually carrying information from one system into the next.
That last part is the real test. A tool that automates one step but still requires manual handoff to the next isn’t automating the workflow. It’s automating a task. Those are different things, and the difference shows up directly in how much time a practice actually gets back.
Where Most Practices Still Do Things by Hand
A few friction points show up again and again in clinics that haven’t automated the full workflow yet:
Scheduling and reminders that exist in one system, disconnected from the patient’s actual history or upcoming visit prep.
Documentation that a physician has to write or dictate separately, then someone else has to translate into billing codes later.
Prior authorizations that require a phone call, a fax, or a portal login — sometimes all three — for something that should be a formality.
Claims that get denied for coding errors that a connected system would have caught before submission, not after.
Each of these, handled individually, eats maybe ten or fifteen minutes. Multiply that across every patient, every day, and it’s not hard to see where the extra two hours after clinic close actually comes from.
What Changes When Documentation Becomes Part of the Workflow, Not a Separate Task
This is where AI clinical documentation software earns its place in the conversation, and it’s worth separating from the rest of the workflow for a second, because it tends to be the piece physicians feel most directly.
The old version of documentation is well known to every practicing physician: type or dictate the note, often after the visit, sometimes hours later, reconstructing details from memory. Even a good memory loses something in that gap.
Real workflow automation changes where documentation sits in the process. Instead of being something a physician does after the workflow, it becomes the first step of the workflow — captured during the actual conversation, structured immediately, and passed forward into coding and billing without anyone re-typing it. The physician still reviews and confirms it, the way any clinical documentation should be reviewed. What disappears is the blank-page problem of writing it all from scratch after the fact.
A Day That Actually Runs This Way
It’s easier to picture concretely than to describe abstractly. A patient arrives for a follow-up. Their history and any prior authorization needs were already checked before they walked in. During the visit, the physician talks and examines without stopping to type — the conversation itself becomes the documentation, captured accurately as it happens. After the visit, that same note flows into coding suggestions and a submitted claim, without a separate step for anyone in the office to handle by hand.
Multiply that across twenty or thirty visits, and it’s not one dramatic time-save. It’s a dozen small handoffs that simply stop existing.
What to Look for Before Adopting It
A few honest questions tend to separate real workflow automation from a tool wearing the label:
- Does information move between steps automatically, or does staff still have to carry it manually?
- Does documentation flow directly into coding and billing, or stop at the note?
- Does it fit into the EHR and systems the practice already uses?
- What happens to a claim that would otherwise be denied — is anything actually catching it beforehand?
If a vendor can’t answer those clearly, the “automation” claim is usually thinner than it sounds.
Where This Fits at AllayAI
This is the exact gap HELIX was built to close. Documentation starts the moment a visit does, functioning as AI clinical documentation software that captures the conversation in real time rather than requiring it to be reconstructed afterward. That same documentation flows forward automatically — into coding suggestions, prior authorization handling, and claims — as one connected workflow rather than a set of separate tools a staff member has to manage individually. It’s built on HIPAA-compliant infrastructure, with the same security standard applied to every stage of that process.
Healthcare workflow automation isn’t really about any single clever feature. It’s about how many fewer times a piece of information has to be typed twice before a patient’s visit is actually finished — for the practice, and for the physician heading home at a reasonable hour.
Frequently Asked Questions
What is healthcare workflow automation, in plain terms? It’s when the steps of a patient visit — scheduling, documentation, coding, billing — move forward automatically and stay connected, instead of requiring staff to manually transfer information between separate systems.
How is AI clinical documentation software different from a regular dictation tool? Dictation tools convert speech to text, which still needs to be reviewed and restructured into a proper clinical note. AI clinical documentation software captures the visit in structured, clinically accurate form as it happens, so far less manual cleanup is needed afterward.
Does workflow automation replace clinical judgment? No. It handles the administrative and documentation steps around a visit — it doesn’t diagnose, treat, or make clinical decisions. The physician remains fully in control of the visit itself.
Will healthcare workflow automation work with the EHR my practice already uses? A genuine workflow automation platform should integrate with your existing EHR rather than requiring you to replace it. That’s worth confirming directly with any vendor before adopting one.